
Rare airway disease and bronchial casts
Plastic Bronchitis: Symptoms, Causes, Diagnosis and Treatment
Plastic bronchitis is a rare condition in which firm, branching material forms inside the airways. These bronchial casts can partially or completely obstruct airflow and may occasionally cause a medical emergency.
- Bronchial casts
- Fontan circulation
- Lymphatic disease
- Eosinophilic inflammation
- Bronchoscopy
- DCMRL
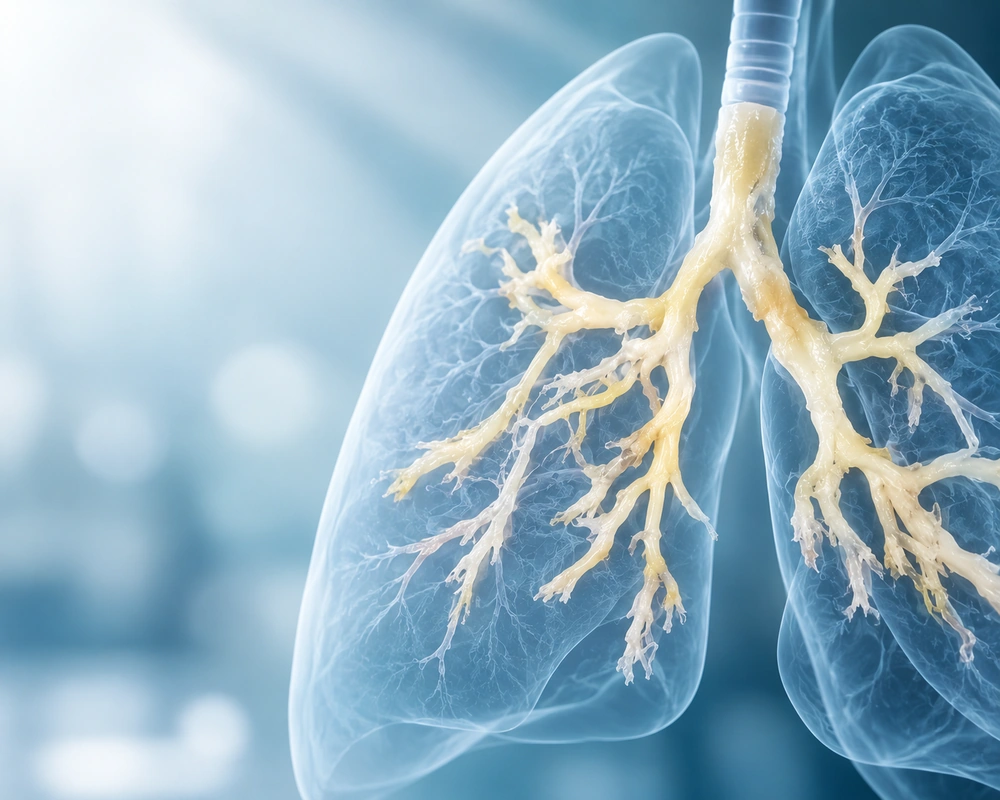
Cast removal is only part of treatment
Removing a cast may immediately restore airflow, but preventing recurrence requires investigation of why the cast formed.
Large casts can obstruct major airways
Severe breathlessness, cyanosis, confusion or rapidly worsening respiratory distress requires emergency medical attention.
What is plastic bronchitis?
Despite its name, plastic bronchitis has nothing to do with plastic material. The word “plastic” describes the moulded, firm shape of the casts.
The casts are different from ordinary sputum. Depending on the underlying mechanism, they may contain fibrin, mucus, inflammatory cells, lymphatic fluid and other proteins.
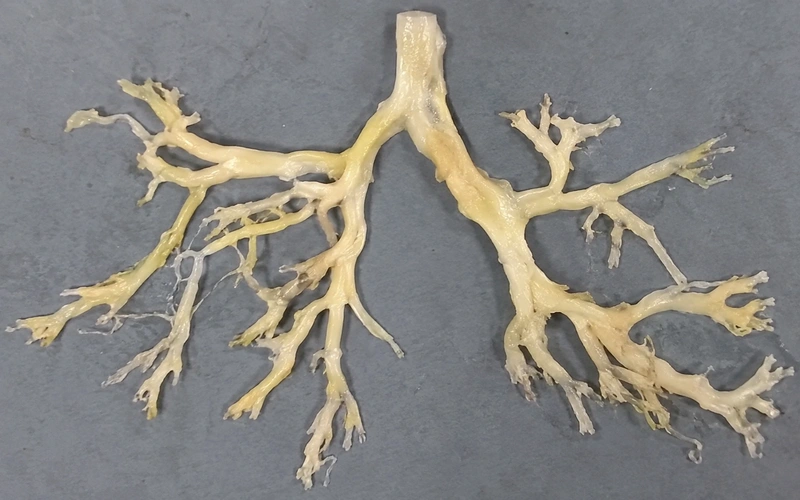
A characteristic feature
More than unusually thick mucus
A patient may cough out an intact branching cast or several smaller fragments. The casts can look strikingly similar to part of the bronchial tree because they mould themselves to the shape of the airways.
Colour can vary from white or cream to tan or occasionally blood-stained. Their consistency may be firm, rubbery or gelatinous.
Not one disease mechanism
What causes plastic bronchitis?
Plastic bronchitis can develop in several different clinical settings. Modern research increasingly recognises that different biological mechanisms may produce superficially similar bronchial casts.
A clinically useful distinction is between lymphatic plastic bronchitis and eosinophilic or inflammatory plastic bronchitis.
Abnormal lymphatic flow
Protein-rich lymphatic fluid may travel through abnormal channels towards the lungs and leak into the airways.
This mechanism is particularly important in people with congenital heart disease and Fontan circulation.
Eosinophilic airway inflammation
Some casts contain large numbers of eosinophils, immune cells associated with allergic and type 2 inflammatory disease.
Asthma and related airway inflammation may be important in this group.
Why the distinction matters
Treatment aimed at abnormal pulmonary lymphatic flow is very different from treatment aimed at eosinophilic airway inflammation. Understanding the underlying mechanism can therefore directly influence management.
Lymphatic abnormalities, congenital heart disease and Fontan surgery
The lymphatic system collects excess fluid from tissues and eventually returns it to the bloodstream. In some patients, lymphatic fluid flows abnormally towards the lungs.
Plastic bronchitis has a particularly important association with congenital heart disease in patients who have undergone the Fontan procedure.
The Fontan operation is used for selected complex congenital heart conditions involving a single functional ventricle. Changes in venous pressure and lymphatic circulation after Fontan surgery can place additional stress on the lymphatic system.
Plastic bronchitis remains uncommon even after Fontan surgery
It is nevertheless an important recognised complication because severe cast formation can cause significant airway obstruction.
Other conditions associated with plastic bronchitis
Not every patient has congenital heart disease or an obvious lymphatic abnormality.
Plastic bronchitis symptoms
Symptoms depend on the size, number and location of the bronchial casts and on how much of the airway they obstruct.
A cast obstructing one bronchus may also reduce ventilation to part of the lung. Larger casts can cause more extensive obstruction, oxygen deprivation and respiratory distress.
Airway obstruction can deteriorate rapidly
When is plastic bronchitis an emergency?
A large bronchial cast can obstruct a major airway
Severe or rapidly worsening breathing difficulty requires emergency medical assessment. Do not assume that a cast will pass spontaneously simply because previous episodes have resolved.
How is plastic bronchitis diagnosed?
Diagnosis may begin when a patient coughs up a characteristic branching cast, but further investigation is usually needed to identify the underlying mechanism.
Standard chest imaging can help assess the lungs, but it does not always reveal the underlying lymphatic abnormality responsible for cast formation.
Where appropriate, London Chest Specialist can arrange chest imaging and CT assessment as part of a respiratory investigation.
Identifying abnormal pulmonary lymphatic flow
The role of dynamic contrast MR lymphangiography
When lymphatic plastic bronchitis is suspected, specialised lymphatic imaging can provide information that ordinary chest imaging cannot.
During DCMRL, contrast material is introduced into the lymphatic system and MRI is used to follow its movement.
The technique can demonstrate abnormal lymphatic pathways and show lymph travelling towards the lungs.
In selected patients, this information can then guide a targeted lymphatic intervention.
Why this has changed treatment
Advanced lymphatic imaging has shifted some cases of plastic bronchitis from symptom management towards identifying and treating the abnormal pathway responsible for lymph leaking into the airways.
How is plastic bronchitis treated?
Immediate airway management
Large casts may require bronchoscopy to reopen an obstructed airway and restore ventilation.
Some patients require repeated bronchoscopies when casts recur.
Mechanism-based treatment
Longer-term treatment depends on whether the problem is primarily lymphatic, eosinophilic, inflammatory, cardiac or related to another underlying condition.
Specialist supervision is essential
Treatments such as nebulised alteplase or heparin are specialised therapies and should not be attempted without appropriate respiratory or specialist-team supervision.
Treating eosinophilic plastic bronchitis
If bronchial cast analysis demonstrates prominent eosinophilic inflammation, management may focus more directly on the underlying inflammatory airway process.
This can include optimisation of asthma or other type 2 inflammatory airway disease.
Emerging research has also explored targeted biological medicines in selected inflammatory cases. Evidence remains limited, however, and there is not yet one standardised biologic treatment pathway for plastic bronchitis.
Patients with asthma-related symptoms may also benefit from specialist assessment through the London Chest Specialist asthma service .
One of the most important advances in lymphatic disease
Selective lymphatic embolisation
In patients with lymphatic plastic bronchitis, specialised imaging may identify abnormal vessels carrying lymph towards the lungs.
An interventional specialist can sometimes close selected abnormal lymphatic channels using a procedure known as selective lymphatic embolisation.
Why this matters
Published reports describe substantial symptom improvement in many treated patients with congenital heart disease and abnormal pulmonary lymphatic flow, although studies remain relatively small because plastic bronchitis is rare.
Managing heart circulation in Fontan-associated disease
In patients with Fontan circulation, treatment is not limited to the lungs or lymphatic system.
Cardiology teams may assess heart function, venous pressure and haemodynamics to identify factors that increase lymphatic pressure or interfere with lymphatic drainage.
Correcting significant circulatory problems can therefore form an important part of the wider treatment plan.
Can plastic bronchitis come back?
Yes. Plastic bronchitis can recur.
Some patients have a single episode, while others repeatedly produce bronchial casts.
Removing the cast does not necessarily treat the cause
Bronchoscopy can restore airflow immediately, but recurrence can continue if abnormal lymphatic flow, eosinophilic inflammation or another underlying mechanism remains active.
This is why recurrent episodes usually warrant specialist investigation rather than repeated cast removal alone.
What is the outlook for plastic bronchitis?
The outlook varies considerably depending on the mechanism, severity of airway obstruction and whether the underlying cause can be controlled.
Severe disease can be life-threatening
A large cast obstructing a major airway can cause severe hypoxia and respiratory failure.
Immediate airway management can therefore be critical.
Depending on the case, care may involve respiratory physicians, cardiologists, interventional radiologists, lymphatic specialists and intensive care teams.
Moving from appearance to mechanism
The changing understanding of plastic bronchitis
Plastic bronchitis was historically classified largely according to how bronchial casts appeared under a microscope.
Cast composition remains useful, but newer research increasingly emphasises identifying the biological mechanism responsible for cast formation.
Look for abnormal pulmonary lymphatic flow
These patients may benefit from sophisticated lymphatic imaging and, in selected cases, targeted lymphatic intervention.
Investigate airway inflammation
These patients may require detailed assessment and treatment of asthma, eosinophilic inflammation or another inflammatory airway disorder.
Mechanism-based treatment is increasingly important
Advanced lymphatic imaging, immunological assessment and mechanism-based treatment are increasingly important in the evaluation of recurrent or complex plastic bronchitis.
Frequently asked questions
Is plastic bronchitis the same as ordinary bronchitis?
No. Ordinary bronchitis describes inflammation of the bronchial tubes, commonly associated with infection or irritation. Plastic bronchitis involves the formation of firm bronchial casts that can reproduce the shape of the airways and cause obstruction.
What does a plastic bronchitis cast look like?
A bronchial cast often looks like a thick, rubbery or gelatinous branching structure. It may resemble part of a small tree because it takes the shape of the bronchial tubes. Colour and consistency vary according to its composition and underlying cause.
Is plastic bronchitis dangerous?
It can be. A small cast may cause coughing or wheezing, whereas a large cast can obstruct a major airway and severely reduce oxygen levels. Significant or rapidly worsening breathing difficulty requires emergency medical attention.
Can adults get plastic bronchitis?
Yes. Although plastic bronchitis is well recognised in some children with congenital heart disease, adults can also develop it. Adult disease has been associated with abnormal lymphatic circulation, inflammatory lung conditions, infection and other disorders.
Can plastic bronchitis be cured?
The answer depends on the cause. Removing a cast treats the immediate obstruction, but preventing recurrence requires treatment of the mechanism that caused it. Selected patients with abnormal lymphatic flow may improve substantially after targeted lymphatic intervention, while others need ongoing treatment of heart disease, asthma or airway inflammation.
The bottom line
Plastic bronchitis is a rare but potentially serious condition in which branching casts form inside the airways.
The immediate danger is airway obstruction. Bronchoscopy may be required to remove a cast and restore ventilation.
Long-term management depends on identifying why casts are forming. In some patients the main problem is abnormal pulmonary lymphatic flow, particularly after Fontan surgery. In others, eosinophilic or inflammatory airway disease is more important.
Advanced lymphatic imaging, including DCMRL, has substantially improved the investigation of lymphatic disease and can help guide selective lymphatic embolisation in suitable patients.
Recurrent disease therefore benefits from a mechanism-based, multidisciplinary approach rather than repeated cast removal alone.
Related respiratory information
- London Chest Specialist. Asthma diagnosis and treatment. Explore the asthma service
- London Chest Specialist. Chest infection diagnosis and treatment. Explore the chest infection service
- London Chest Specialist. CT scan and chest imaging. Explore chest imaging
- London Chest Specialist. Lung function tests. Explore lung function testing

Unusual Airway Casts or Persistent Respiratory Symptoms?
Specialist respiratory assessment can help investigate airway obstruction, recurrent cast formation, asthma, unusual airway inflammation and abnormalities seen on chest imaging.
